
info@mail.ucallm.com
Severe Acute Respiratory Syndrome Coronavirus 2 (SARS‑CoV‑2) Research
1. Overview
Severe acute respiratory syndrome coronavirus 2 (SARS‑CoV‑2) is a positive‑sense single‑stranded RNA virus belonging to genus Betacoronavirus, subgenus Sarbecovirus. It is the causative agent of coronavirus disease 2019 (COVID‑19). First reported in Wuhan, China, in late 2019, SARS‑CoV‑2 spreads predominantly via respiratory droplets and aerosols. The incubation period commonly ranges from 2‑14 days. Infected persons can transmit the virus even before symptom onset. Clinical presentations vary widely: asymptomatic infection, mild upper‑respiratory symptoms, moderate pneumonia, or severe disease with acute respiratory distress syndrome (ARDS), cytokine storm, multi‑organ injury and death. Age and underlying comorbidities are major risk factors for severe outcomes. The virus has generated multiple variant lineages with altered transmissibility, immune evasion, or clinical characteristics.
2. Background Information
2.1 What is SARS‑CoV‑2?
SARS‑CoV‑2 is an enveloped positive‑sense single‑stranded RNA virus within Coronaviridae family, Orthocoronavirinae subfamily, Betacoronavirus genus, Sarbecovirus subgenus. Its genome size is approximately 29.9 kb. Genome architecture includes a 5'‑UTR, large replicase ORF1a/ORF1b region, structural‑protein genes, accessory open reading frames, a 3'‑UTR and poly(A) tail.
The 5’ two‑thirds of the genome encodes pp1a and pp1ab polyproteins, cleaved by viral proteases to yield 16 non‑structural proteins (nsp1‑nsp16). These nsps assemble replication‑transcription complexes (RTC) for viral RNA synthesis, modification, proofreading and host immune antagonism.
The 3’ genomic segment encodes four canonical structural proteins: Spike (S), Envelope (E), Membrane (M), Nucleocapsid (N), plus multiple accessory proteins (ORF3a, ORF3b, ORF6, ORF7a, ORF7b, ORF8, ORF9b etc.). Spike mediates host‑cell receptor recognition and membrane fusion. N protein packages viral genomic RNA. M and E participate in virion morphogenesis, assembly and egress.
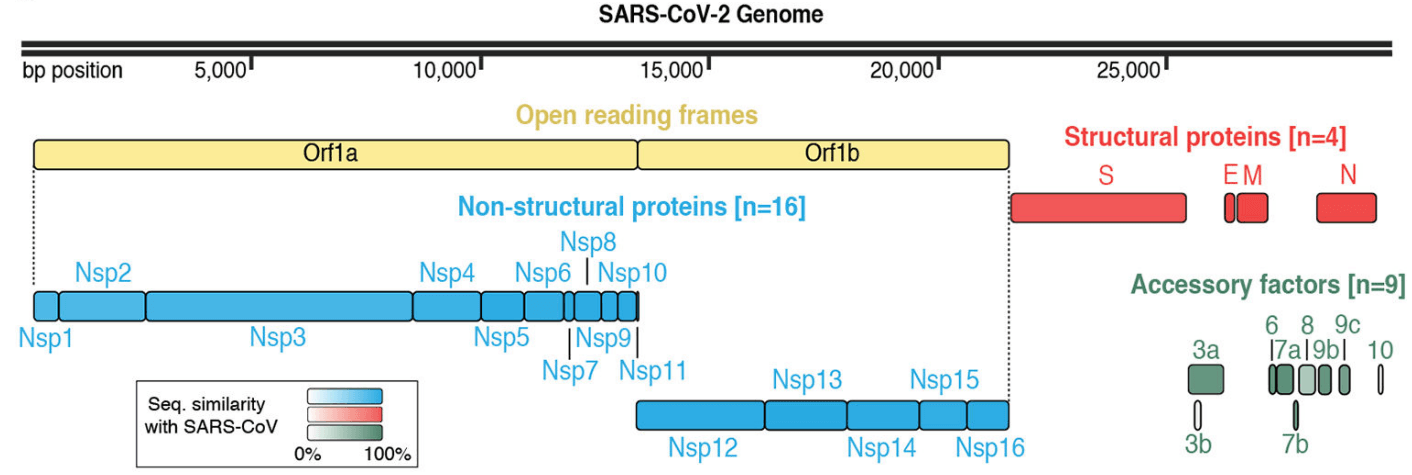
SARS‑CoV‑2 genome organization (PMID: 32015508)
2.2 SARS‑CoV‑2 Genome & Variants
| Genome Region | Major Products | Main Function |
|---|---|---|
| ORF1a | pp1a → nsp1‑11 | Replication complex assembly, host‑cell modulation |
| ORF1b | pp1ab → nsp12‑16 | RNA‑dependent RNA synthesis, RNA proofreading & modification |
| S | Spike glycoprotein | Receptor binding, host‑membrane fusion |
| ORF3a | ORF3a accessory protein | Ion‑channel activity, host‑pathogen interaction |
| E | Envelope protein | Virion assembly, ion‑channel function |
| M | Membrane protein | Virion morphogenesis & assembly |
| ORF6 | ORF6 | Host‑immune antagonism |
| ORF7a / ORF7b | Accessory proteins | Host‑cell interaction, immune modulation |
| ORF8 | ORF8 | Immune evasion, host‑protein degradation |
| N | Nucleocapsid protein | Viral RNA binding, genome packaging |
Major Variant Lineages
| Variant Group | Key Spike Mutations | Phenotypic Features |
|---|---|---|
| Alpha (B.1.1.7) | Δ69‑70, Δ144, N501Y, A570D, P681H, T716I, S982A, D1118H | Increased transmissibility |
| Beta (B.1.351) | D80A, D215G, Δ242‑244, K417N, E484K, N501Y | Enhanced antibody escape |
| Gamma (P.1) | L18F, T20N, P26S, D138Y, R190S, K417T, E484K, N501Y, H655Y | Antibody escape & increased transmission |
| Delta (B.1.617.2) | T19R, Δ156‑157, R158G, L452R, T478K, P681R, D950N | Strongly enhanced transmissibility |
| Omicron (B.1.1.529) | Extensive spike‑protein mutations including many within RBD | Marked immune evasion, altered tissue tropism |
2.3 SARS‑CoV‑2 Structural Proteins
Four major structural proteins: Spike (S), Envelope (E), Membrane (M), Nucleocapsid (N). Spike glycoprotein is the main surface antigen and mediates host‑cell entry. S protein is cleaved into S1 and S2 subunits. S1 contains Receptor‑Binding Domain (RBD) for ACE2 receptor binding; S2 executes membrane‑fusion events. N protein binds viral RNA for genome packaging, also participates in replication‑transcription and host‑cell interactions. M and E coordinate virion assembly, budding and release.
Structural Protein Targets
| Protein | Full name | Main Function |
|---|---|---|
| S | Spike protein | ACE2 receptor binding and membrane fusion |
| S1 | Spike S1 subunit | Receptor recognition |
| RBD | Receptor‑binding domain | Direct ACE2 interaction |
| S2 | Spike S2 subunit | Membrane fusion machinery |
| N | Nucleocapsid protein | RNA binding, genome packaging |
| M | Membrane protein | Virion assembly |
| E | Envelope protein | Assembly, release, viroporin activity |
2.4 Mechanism of Cell Entry and Replication Cycle
2.4.1 Receptor Recognition and Attachment
SARS‑CoV‑2 Spike protein binds human angiotensin‑converting enzyme 2 (ACE2). RBD within S1 is responsible for high‑affinity interaction with ACE2. Host co‑factors include TMPRSS2, cathepsins, heparan sulfate and other attachment molecules; ACE2 remains the primary functional receptor.
2.4.2 Spike Protein Priming and Activation
Two major proteolytic routes: cell‑surface TMPRSS2 cleavage of Spike after ACE2 engagement triggers early plasma‑membrane fusion; alternatively virions are endocytosed and endosomal cathepsin‑B/L mediate S‑protein activation inside endosomes for fusion with endosomal membrane.
2.4.3 Viral RNA Replication & Transcription
After fusion and uncoating, positive‑sense genomic RNA is released into cytosol. Host ribosomes translate pp1a and pp1ab polyproteins. Viral proteases (Mpro/nsp5, PLpro/nsp3) process polyproteins to produce nsp1‑16 non‑structural proteins. These assemble RTC replication‑transcription complexes for negative‑strand intermediate synthesis, then produce full‑length genomic RNA plus nested set of subgenomic RNAs coding structural and accessory proteins.
2.4.4 Virion Assembly and Egress
New‑synthesized positive‑sense genomic RNA complexes with N protein to form ribonucleoprotein complex. S, M and E structural proteins traffic through secretory pathway to ERGIC compartment. Virion assembly takes place at ERGIC membrane; complete virions are packaged inside transport vesicles and secreted from infected cells.
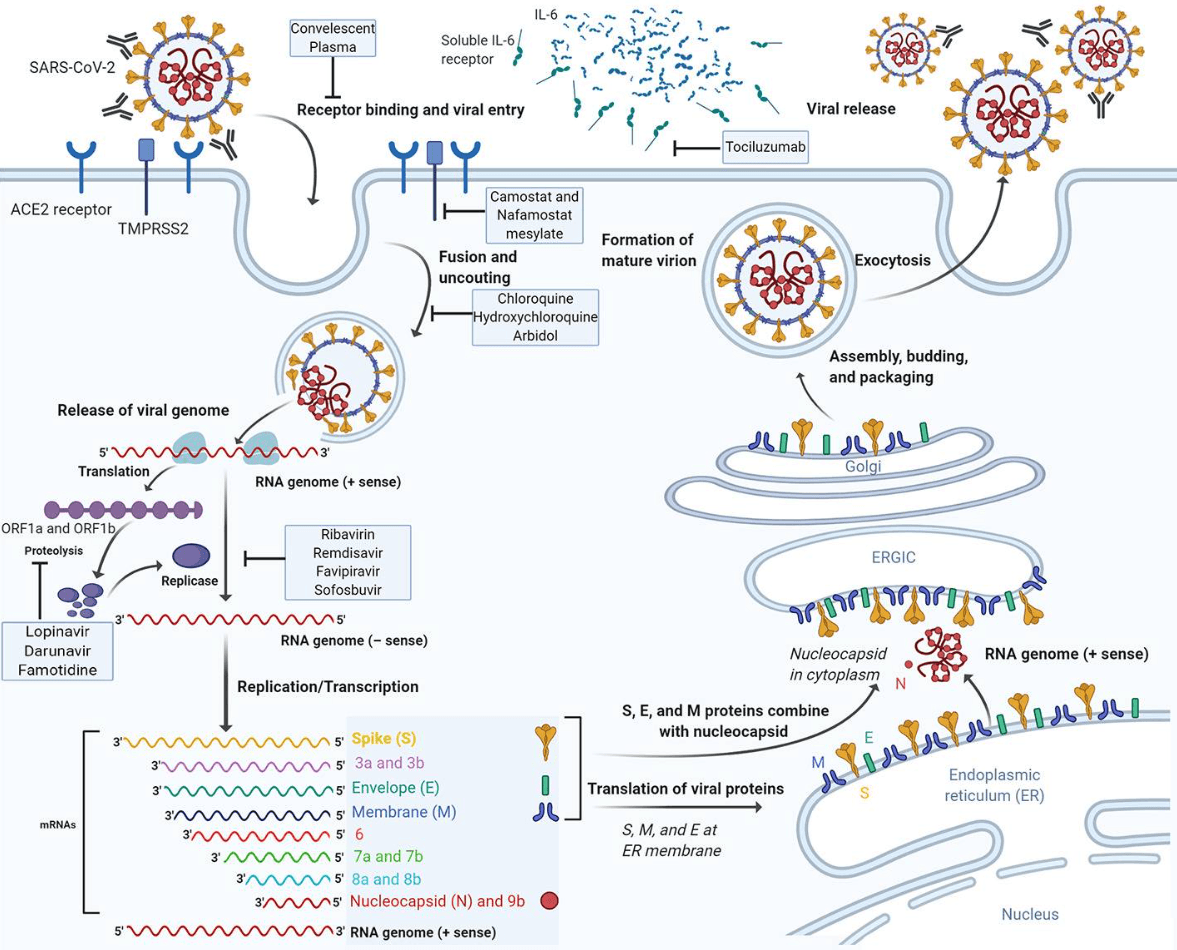
SARS‑CoV‑2 replication cycle overview (PMID: 32265269)
2.5 Clinical Symptoms and Disease Spectrum
SARS‑CoV‑2 infection manifests broad clinical spectrum:
- Asymptomatic infection
- Mild disease: fever, dry cough, sore throat, fatigue, myalgia, headache, loss or alteration of taste/smell, rhinorrhoea, gastrointestinal discomfort
- Moderate disease: lower‑respiratory‑tract involvement, pneumonia, hypoxia
- Severe disease: severe pneumonia, acute respiratory distress syndrome ARDS, cytokine release syndrome, thrombotic events, multi‑organ‑system failure
Long COVID / post‑COVID‑19 syndrome can persist weeks‑months after acute infection, including fatigue, dyspnea, cognitive impairment and diverse systemic manifestations.
2.6 Therapeutic Intervention Targets
2.6.1 Viral‑encoded Targets
| Target | Protein | Biological Role |
|---|---|---|
| Spike (S) | Spike glycoprotein | Receptor binding & membrane fusion |
| RBD | Spike RBD domain | ACE2 interaction |
| S1 subunit | Spike S1 | Receptor recognition |
| S2 subunit | Spike S2 | Membrane fusion |
| N | Nucleocapsid | RNA binding & genome packaging |
| M | Membrane protein | Virion assembly |
| E | Envelope protein | Assembly, viroporin activity |
| Mpro / 3CLpro | nsp5 | Polyprotein processing |
| PLpro | nsp3 | Polyprotein processing & de‑ISGylation |
| RdRp | nsp12 | Viral RNA synthesis |
| Helicase | nsp13 | RNA unwinding |
| ExoN | nsp14 | RNA proofreading |
| nsp16 | nsp16 | mRNA cap‑2'O‑methylation, immune evasion |
2.6.2 Host Receptors & Entry‑Related Factors
| Host Target | Type | Role in Infection |
|---|---|---|
| ACE2 | Receptor | Primary virus receptor for Spike binding |
| TMPRSS2 | Serine protease | Spike protein priming at cell‑surface |
| Cathepsin L | Cysteine protease | Endosomal S‑protein activation |
| Cathepsin B | Cysteine protease | Endosomal S‑protein activation |
| DC‑SIGN / L‑SIGN | C‑type lectin attachment factors | Facilitate viral attachment |
| Heparan sulfate | Cell‑surface glycan | Virus attachment co‑factor |
2.6.3 Host Innate‑Immune & Signalling Pathways
| Pathway | Key Targets | Biological Role |
|---|---|---|
| ACE2‑RAAS axis | ACE2, Ang‑II, AT1R | Virus entry; renin‑angiotensin dysregulation |
| RIG‑I/MDA5‑MAVS | RIG‑I, MDA5, MAVS | Cytosolic viral RNA sensing |
| TBK1‑IRF3 | TBK1, IRF3 | Type‑I interferon induction |
| JAK‑STAT signalling | JAK1, TYK2, STAT1/STAT2 | Interferon downstream signalling |
| TLR‑mediated sensing | TLR3, TLR4, TLR7/8 | Endosomal nucleic‑acid sensing |
| NF‑κB pathway | IKK complex, p65 | Pro‑inflammatory gene expression |
| MAPK inflammatory cascade | ERK, JNK, p38 | Stress‑response & inflammation |
2.6.4 Cytokine / Chemokine Immune Targets
| Target | Category | Major Biological Role |
|---|---|---|
| IFN‑α / IFN‑β | Type‑I interferon | Broad antiviral state induction |
| IFN‑γ | Type‑II interferon | Cell‑mediated immunity |
| IL‑6 | Pro‑inflammatory cytokine | Central mediator of hyper‑inflammation |
| IL‑1β | Pro‑inflammatory cytokine | Inflammasome‑driven inflammation |
| TNF‑α | Pro‑inflammatory cytokine | Multiple inflammatory responses |
| CXCL10 | Chemokine | Recruit immune effector cells |
| CCL2 | Chemokine | Monocyte / macrophage recruitment |
2.7 Vaccine Platforms
Multiple vaccine modalities deployed against SARS‑CoV‑2: mRNA vaccines, viral‑vector vaccines, inactivated whole‑virus vaccines, recombinant protein‑subunit vaccines, DNA‑based vaccines. Most vaccine platforms focus immune responses against Spike glycoprotein, especially RBD domain, to induce neutralizing‑antibody and T‑cell immunity. Variants with extensive spike mutations impose challenges for vaccine effectiveness, driving updates of vaccine antigen composition.
- mRNA vaccines: lipid‑nanoparticle‑delivered mRNA encoding full‑length stabilized Spike protein
- Replication‑defective viral‑vector vaccines: adenovirus vectors encoding Spike antigen
- Inactivated‑virus vaccines: chemically inactivated whole SARS‑CoV‑2 virions
- Recombinant‑protein subunit vaccines: purified Spike / RBD protein antigens plus adjuvant
- DNA vaccines: plasmid‑DNA encoding spike antigen
2.8 Antiviral and Immunomodulatory Therapeutics
2.8.1 Virus‑targeted therapeutics
| Target | Drug / Agent | Mechanism of Action |
|---|---|---|
| Spike‑ACE2 interaction | Neutralizing monoclonal antibodies | Block receptor attachment; neutralize virions |
| Mpro (nsp5) | Nirmatrelvir (ritonavir‑boosted Paxlovid) | Main‑protease inhibition, block polyprotein processing |
| RdRp nsp12 | Remdesivir | Nucleotide analogue; inhibit viral RNA synthesis |
| RdRp nsp12 | Molnupiravir | Nucleoside analogue, introduce viral mutagenesis |
2.8.2 Host‑targeted therapeutics
| Target Pathway / Protein | Drug / Agent | Mechanism of Action |
|---|---|---|
| TMPRSS2 | Camostat mesylate | Inhibit host serine‑protease spike priming |
| IL‑6 receptor | Tocilizumab / Sarilumab | Block IL‑6‑mediated inflammatory signalling |
| JAK‑STAT signalling | Baricitinib | JAK kinase inhibitor, suppress cytokine signalling |
| Glucocorticoid receptor | Dexamethasone | Broad immunosuppressive / anti‑inflammatory effects |
3. Related Products & Services
- Recombinant antigens and receptors (Spike, RBD, N protein, ACE2 etc.)
- Antibody portfolio: neutralizing antibodies, S/N‑protein specific antibodies
- Detection assay kits for antigen / antibody testing
- Recombinant protein custom expression service
- Custom antibody generation service
4. Resources
Global SARS‑CoV‑2 sequence database GISAID; WHO COVID‑19 technical reports; PDB structural repository for coronavirus protein structures.
5. References
- Zhou P, Yang XL, Wang XG, et al. A pneumonia outbreak associated with a new coronavirus of probable bat origin. Nature. 2020;579(7798):270‑273.
- Wu F, Zhao S, Yu B, et al. A new coronavirus associated with human respiratory disease in China. Nature. 2020;579(7798):265‑269.
- Hoffmann M, Kleine‑Weber H, Schroeder S, et al. SARS‑CoV‑2 Cell Entry Depends on ACE2 and TMPRSS2 and Is Blocked by a Clinically Proven Protease Inhibitor. Cell. 2020;181(2):271‑280.e8.
- Wrapp D, Wang N, Corbett KS, et al. Cryo‑EM structure of the 2019‑nCoV spike in the prefusion conformation. Science. 2020;367(6483):1260‑1263.
- Yan R, Zhang Y, Li Y, et al. Structural basis for the recognition of SARS‑CoV‑2 by human ACE2. Science. 2020;367(6485):1444‑1448.
- Wang M, Cao R, Zhang L, et al. Remdesivir and chloroquine effectively inhibit the recently emerged novel coronavirus (2019‑nCoV) in vitro. Cell Res. 2020;30(3):269‑271.
- Owen DR, Allerton CMN, Anderson AS, et al. An oral SARS‑CoV‑2 Mpro inhibitor clinical candidate for the treatment of COVID‑19. Science. 2021;374(6575):1586‑1593.
- Jonsson CM, Jain A. Molnupiravir: A Review of Its Mechanism of Action, Efficacy, and Safety for the Treatment of COVID‑19. Pharmacotherapy. 2022;42(3):247‑258.
- RECOVERY Collaborative Group. Dexamethasone in Hospitalized Patients with Covid‑19. N Engl J Med. 2021;384(8):693‑704.
- RECOVERY Collaborative Group. Tocilizumab in patients admitted to hospital with COVID‑19 (RECOVERY): a randomised, controlled, open‑label, platform trial. Lancet. 2021;397(10285):1637‑1647.
- Bar‑Ziv A, Decaluwe H. COVID‑19 vaccines‑an overview of vaccine platforms, efficacy and variant responses. Curr Opin Virol. 2022;53:101209.
- Harvey WT, Carabelli AM, Jackson B, et al. SARS‑CoV‑2 variants, spike mutations and immune escape. Nat Rev Microbiol. 2021;19(7):409‑424.
- V’kovski P, Kratzel A, Steiner S, et al. Coronavirus biology and replication: implications for SARS‑CoV‑2. Nat Rev Microbiol. 2021;19(3):155‑170.